 Log in


The surgical audit that helped make children’s heart surgery safer
Between 1984 and 1995, more babies died after heart surgery at the Bristol Royal Infirmary than should have, but it took far too long to realise because no systematic, comparable national data on outcomes was being collected. This isn’t just me saying it - the public inquiry which ran from 1998 to 2001 said so directly. One response was to start a new, mandatory, national database of every cardiac operation and interventional catheter performed on a child in the UK: the National Congenital Heart Disease Audit, which has underpinned quality assurance since the early 2000s.
It worked. Alongside surgical and intensive care advances, being able to see outcomes nationally and within hospitals as part of ongoing improvement programmes, has helped drive mortality down. Thirty day mortality after children’s heart surgery in the UK fell from 4.3% in 2000 to 2.6% in 2010, even though the complexity of operations rose. In the national audit’s 2025 report, the 30-day mortality for 2024/25 was just 1.3%. Painstaking national audit of this kind is something the NHS does very well.
But the audit misses a really important group of babies
But every audit has blind spots, and it’s important to understand them because otherwise we risk only focusing what we are measuring and forget about what we cannot see. A baby or child only enters the audit because a procedure happened. Babies diagnosed with a heart defect before or after birth who never had a procedure are not in there, and we have not been tracking what happens to them.
In April 2015, fifteen years after the national database of procedures began, Public Health England launched the National Congenital Anomaly and Rare Disease Registration Service (NCARDRS). NCARDRS registers congenital anomalies wherever in the pregnancy or the first years of life they are picked up: in babies born alive, in stillbirths, in miscarriages, and in terminations at any gestation. It covers more than a thousand different conditions, including congenital heart defects, and has the widest coverage of any congenital anomaly register in the world. It reached full national coverage in 2018.
We saw an opportunity to combine the two datasets to understand for the first time what happens to foetuses and babies diagnosed with congenital heart disease. We linked the two datasets together as well as death registrations from the Office for National Statistics, and followed every detected case of structural congenital heart disease in England with an estimated delivery date in 2018 to 2020, from diagnosis to the first birthday, 11,265 foetuses and babies. Our second peer-reviewed paper has just been published, and I think the findings are both surprising and important. The first paper followed all feotuses and babies. The second looked in detail at the 9,033 babies born alive.
What happens after antenatal diagnosis
64% of cases were detected antenatally, with over 90% detected antenatally for the most complex defects. Detection was lowest (<30%) for defects that are hard to see on a four chamber scan or that develop later in pregnancy.
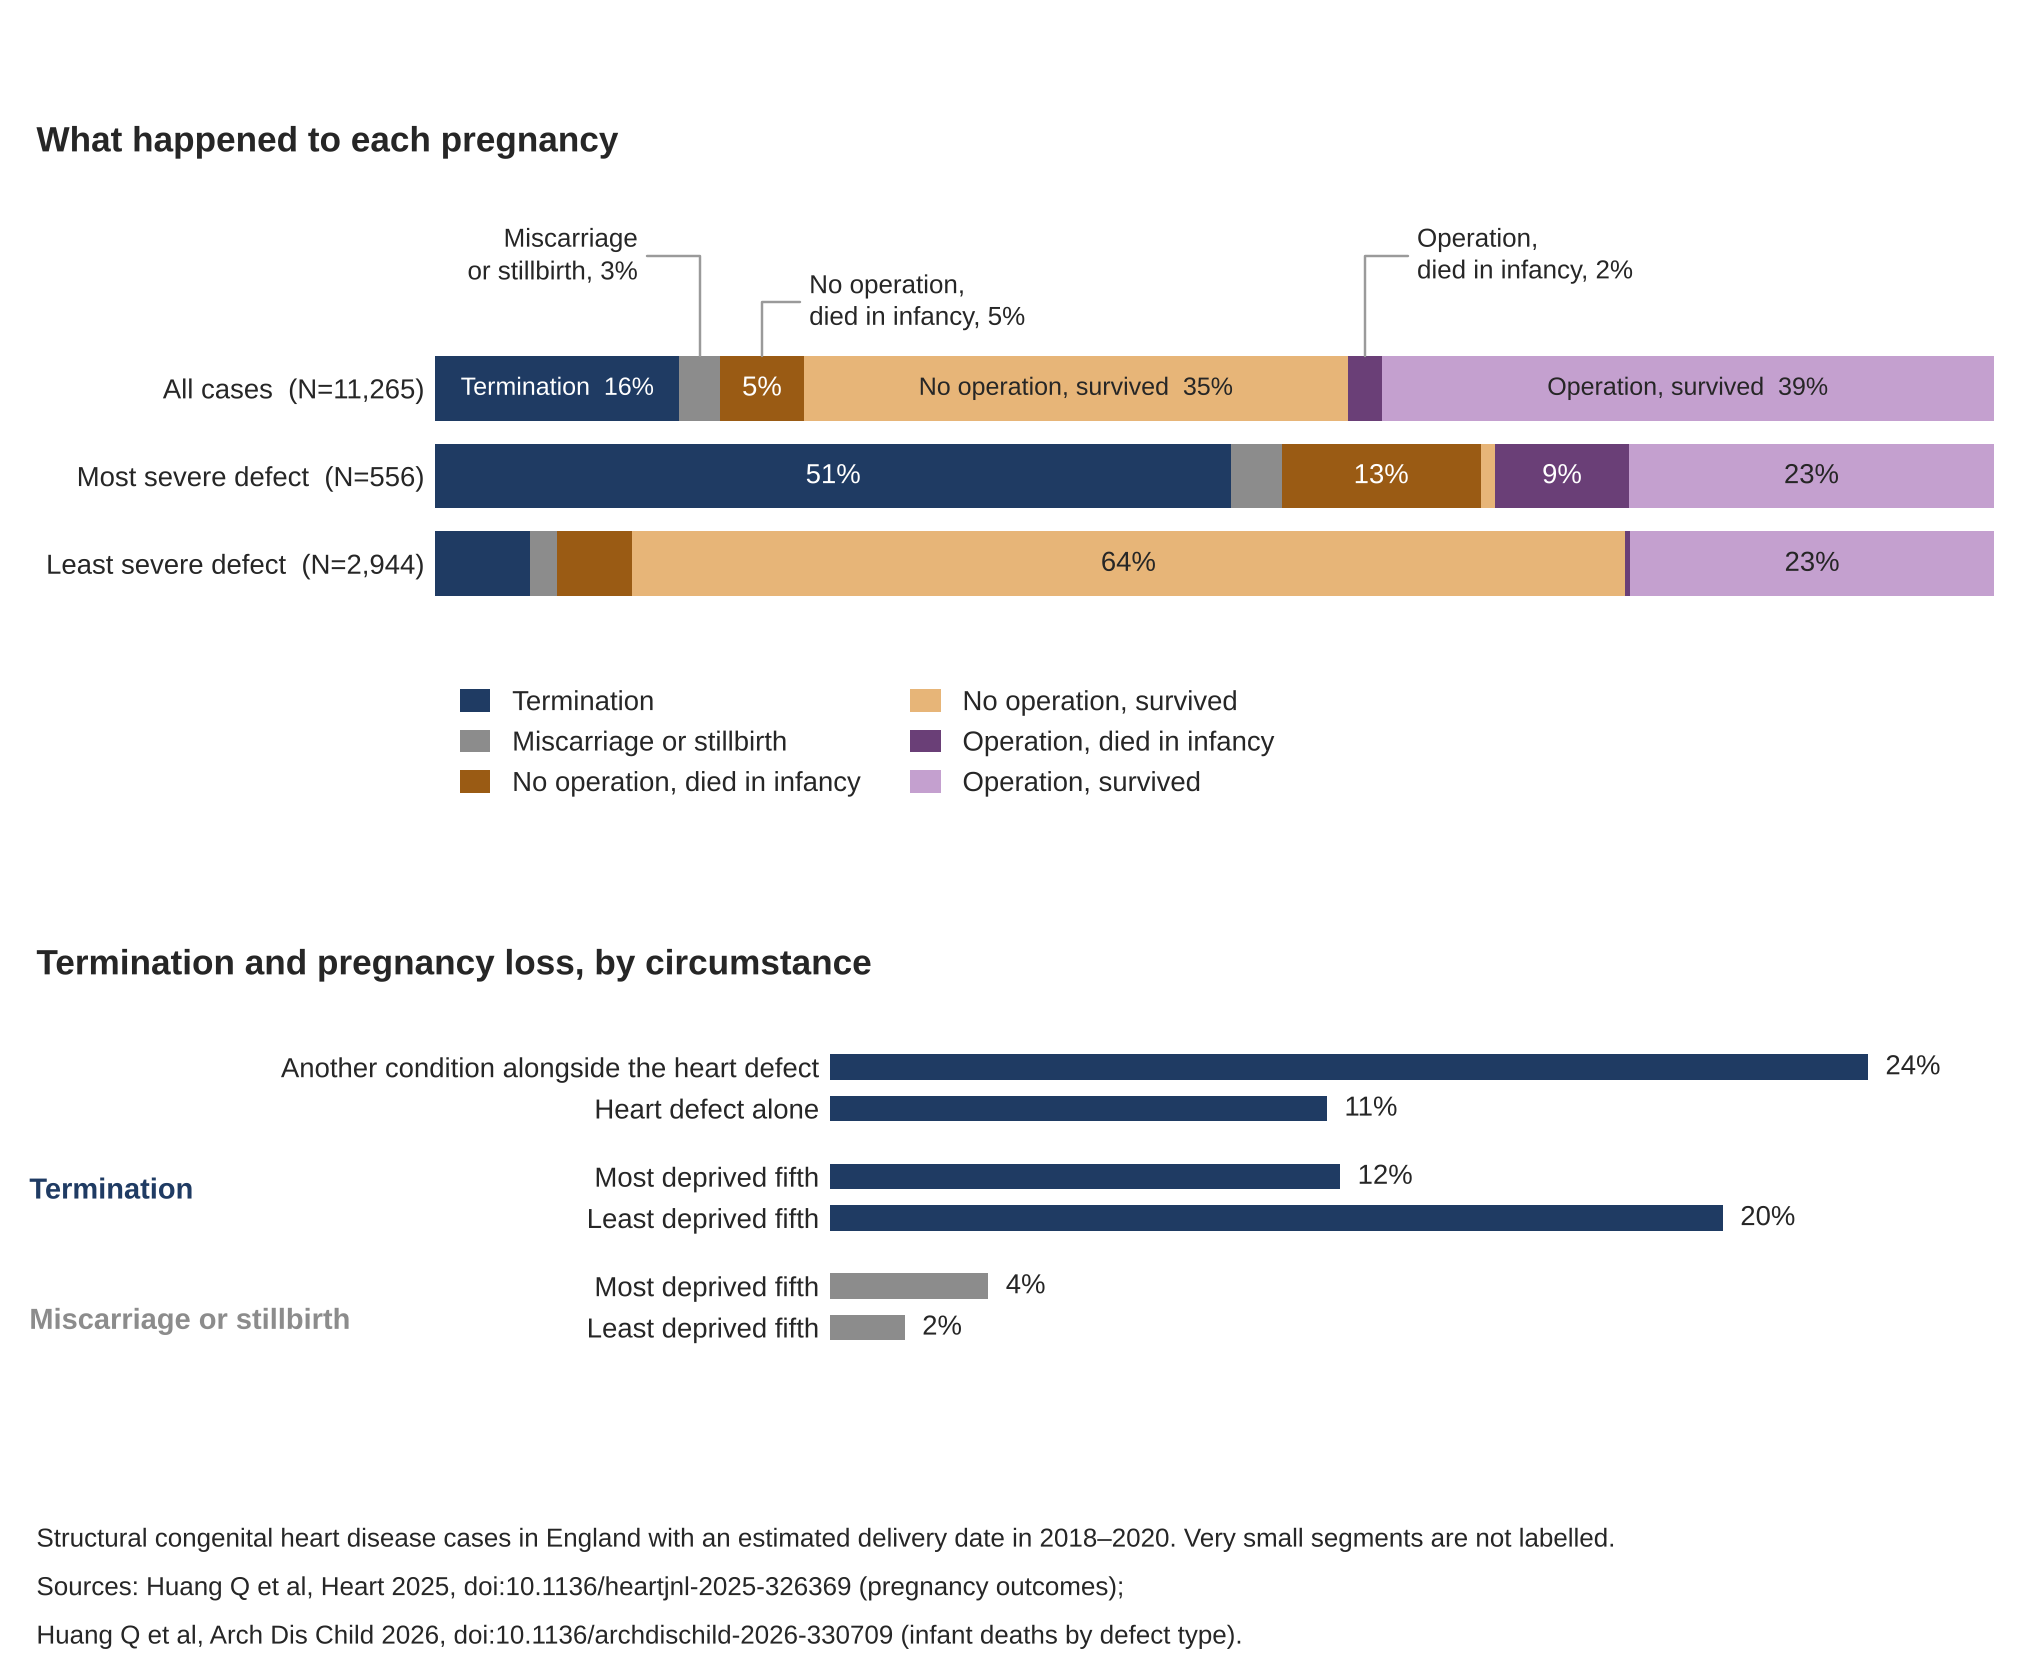
Of the 11,265 cases, 1,766 (16%) ended in termination and 295 (2.6%) in miscarriage or stillbirth. Termination was associated with severity, from 51% of foetuses with the most severe defect undergoing termination to 6% for the least severe. Termination was twice as likely where there was at least one other health problem alongside the heart condition.
Families in the least deprived fifth of neighbourhoods were nearly twice as likely to end the pregnancy as those in the most deprived fifth: 20% vs 12%. Foetal loss had the opposite association: 3.6% in the most deprived fifth vs 1.7% in the least.
This means that babies born alive are more likely to be born to mothers living in deprived communities.
What happens to babies born alive with congenital heart disease
Of 9,033 babies born alive with a structural heart defect, 4,546 (50%) had at least one cardiac intervention before their first birthday. Among the 4,028 babies with a defect classed as severe, 77% had a cardiac intervention before their first birthday.
The other half had no procedure in that first year. Some babies are too well to need one yet. Isolated ventricular septal defect (a hole between the two main chambers of the heart) is the largest group in the non-intervened group: 2,016 babies with no intervention in the first year of life. Many of these holes close on their own or don’t need to be closed straight away, allowing babies to grow stronger before having surgery.
On the other hand, some babies are too sick or too complex to have surgery in their first year, or are on a palliative care pathway chosen with their families. Of 105 babies with the three most severe defects who had no intervention in their first year of life, 95 sadly died before their first birthday.
The deaths we are just not tracking
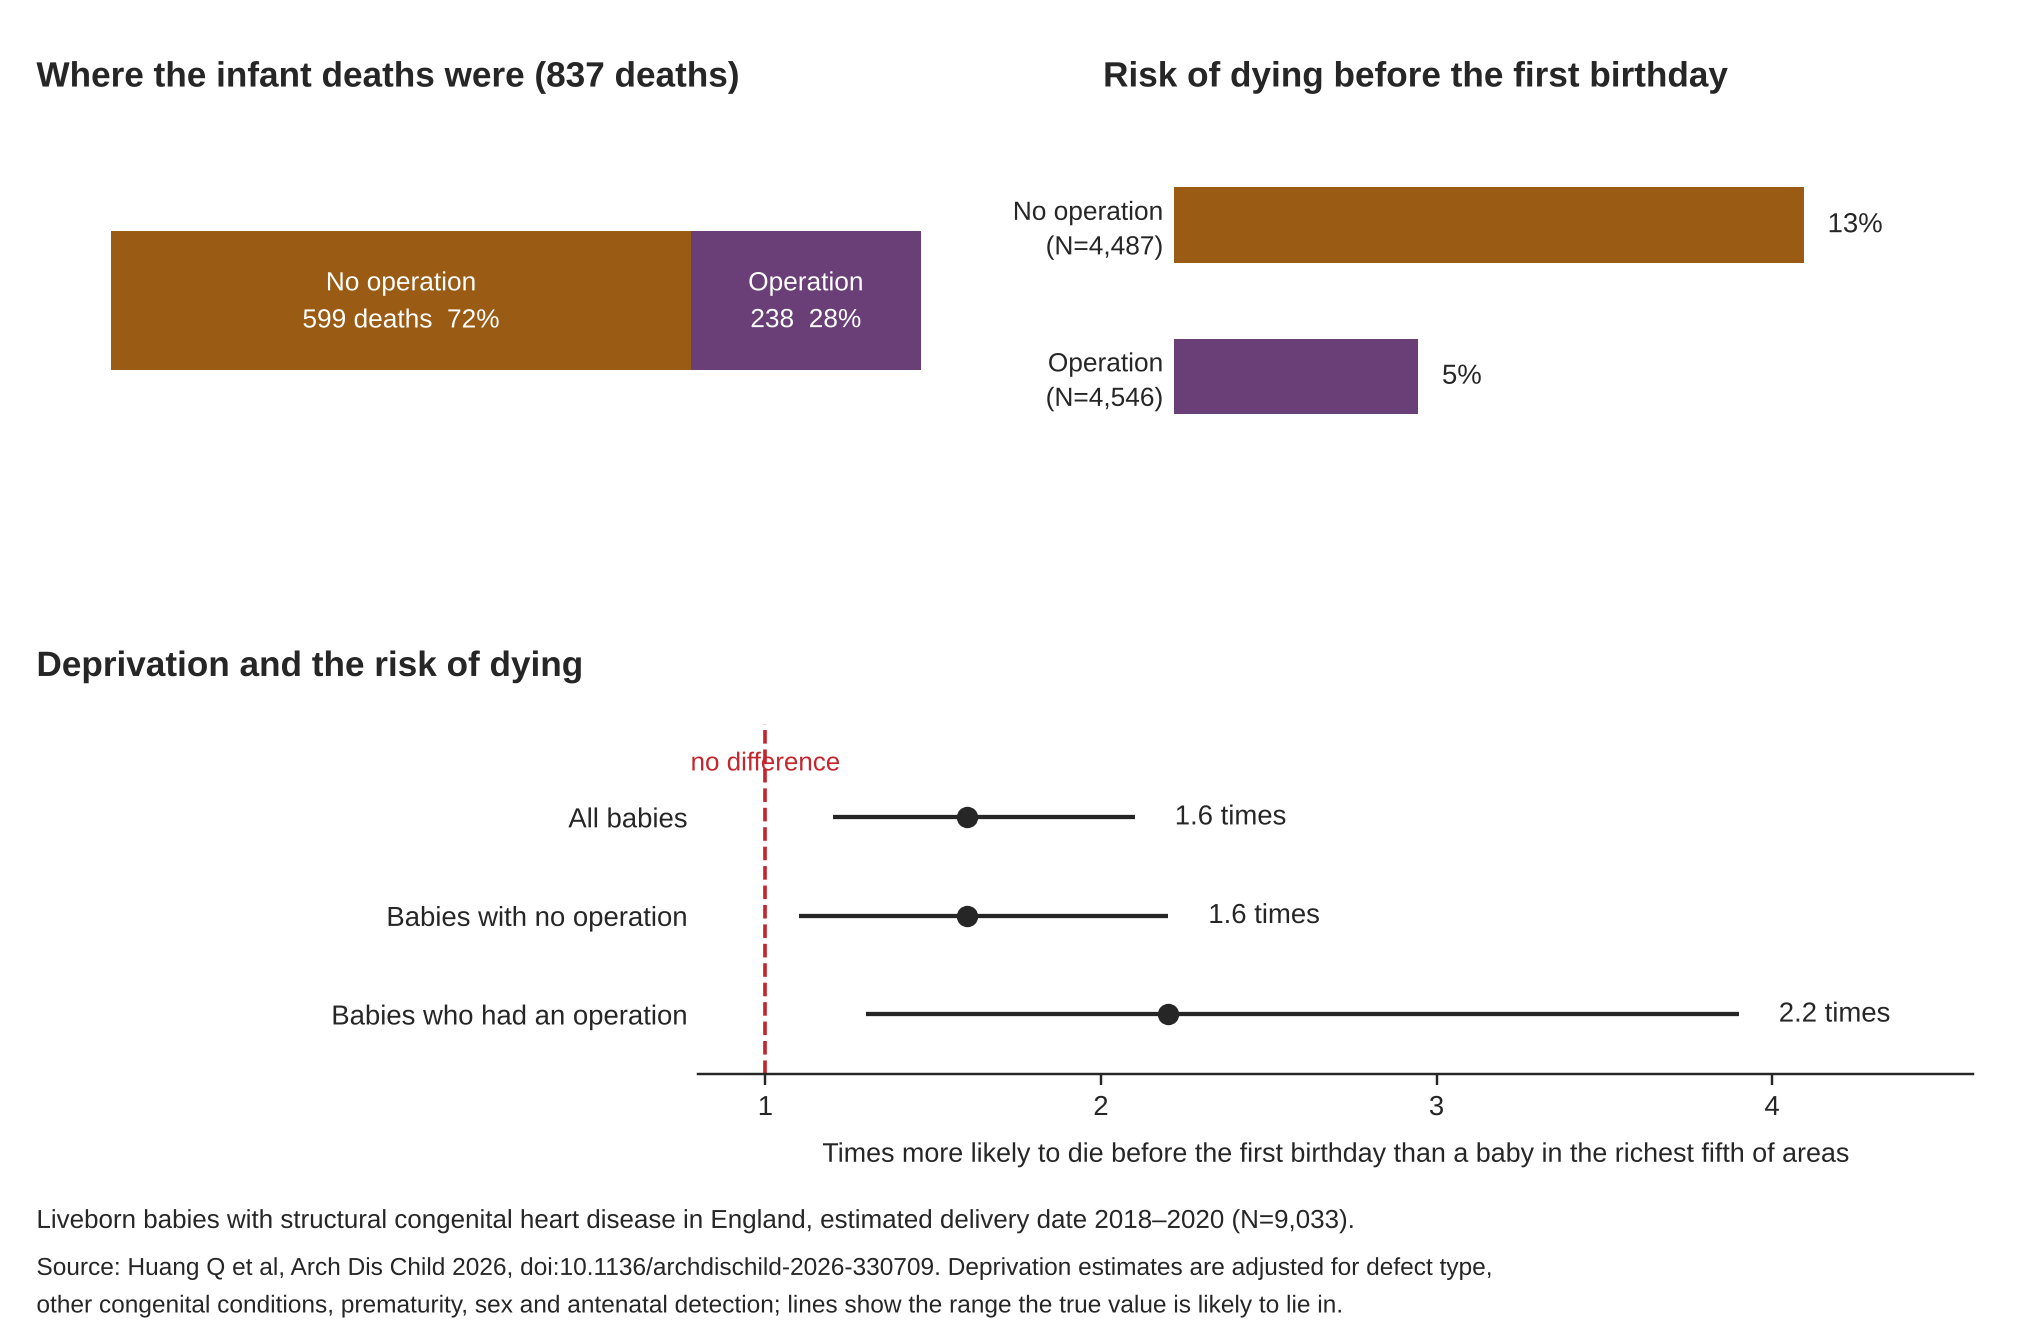
What our research really showed was the importance of looking at the whole picture – because looking just at babies who received an intervention (especially if looking only at deaths within a month of surgery), simply misses too much information. Overall, 837 of the 9,033 babies born alive died before their first birthday (9%). Of those deaths, 599 (72%) were in babies with no cardiac intervention, and so would not have been picked up in the national audit based on interventions. Infant mortality was 13% in the non-intervened group against 5% among babies who were operated on.
We tested whether impaired access to care was a possible explanation for the difference between deaths with and without an intervention in the first year of life. If it might be, we would expect to see that babies who died without an operation would have been less likely to have an antenatal diagnosis and more likely to be born in a more deprived area compared to those who died after an operation. We saw neither association.
Medical complexity does seem to be a likely explanation for the difference. Comparing deaths in babies without an operation to deaths after one, 60% vs 49% had an additional non cardiac congenital condition, and 50% vs 29% were premature (a big risk factor). This pattern holds across the spectrum of severity for defects.
Deprivation was also important. Babies born in the poorest fifth of neighbourhoods were about 60% more likely to die before their first birthday than babies in the richest fifth, once differences in the defect itself, other conditions, prematurity, sex and whether it was found before birth were accounted for. This was true whether the baby had a procedure or not. The data do not allow us to understand why, but they do suggest that this should be an area of future research focus.
The surgical audit was started to monitor surgical outcomes and to try to ensure that any concerns about quality of surgical care can be picked up quickly. But that means only looking at deaths within a short time of surgery and missing babies that died later after surgery (which could be for a number of reasons) or those not operated on at all. I believe that these latter deaths are important to track for two reasons: firstly providing families with better information about what might happen on first diagnosis, and secondly, so that the NHS can learn to improve outcomes for these babies. This could be by improving decisions around which babies receive an operation, by improving support for children and families who do not receive an intervention, or by improving support once babies go home after surgery, particularly for those living in more deprived communities.
So what next
Routinely report on the non intervention pathway. These babies and their families are receiving care, including palliative care, and to our knowledge their outcomes are not being systematically reviewed anywhere.
Understand more about why babies had no operation. Futility, parental choice, and a defect that simply did not need fixing yet are categorically different things that show up the same way in the data – to separate them and, importantly, understand them, we need new prospective research studies working with clinicians and families.
Understand what’s behind more deaths in deprived areas. We see significant differences between most and least deprived areas for termination rates, foetal loss, and in infant death with and without surgery. Understanding why is crucial if we want to improve outcomes for babies born in more deprived areas.
Keep (and expand) the surgical audit. Counting what happens to operated babies was, and is, a good thing and has helped drive improvements in survival for these babies. As mortality rates have come down, we should add other outcomes to the audit (such as complications after surgery, which has already started), to support services to keep improving.
I don’t often write about my academic research on Substack, but I thought this work was a really good example of how clinical audits can support improved care but also how important it is to try to understand the whole picture – and how different perspectives on the same data can really provide new insights.





