plant lover, cookie monster, shoe fiend
20981 stories
·
20 followers

Chronic Pain Costs Canada More than Cancer. But There’s a Fix | The Tyee

1 Share

British Columbia needs to catch up on both low-barrier and specialty care for chronic pain, according to Maria Hudspith, CEO of Pain BC and former co-chair of the Canadian Pain Task Force.

In 2021 the Canadian Pain Task Force published an action plan with six overarching goals and 150 recommendations to overhaul how the country treated pain.

In 2019 Health Canada estimated chronic pain costs the country between $38.2 billion and $40.3 billion in health-care costs and lost productivity in the workforce.

It’s the greatest cause of disability in Canada and the primary reason people leave the workforce. It also dwarfs the economic impacts of cancer and heart disease, Hudspith said.

The number of Canadians living with chronic pain will most likely increase as the population ages.

Five years after the action plan was published, there has been a lot of progress on 120 of the 150 recommendations, Hudspith said. Nine provinces have introduced pain strategies, invested in new pain services, expanded access to pain care and improved the education of health-care professionals when it comes to pain.

In B.C. the Provincial Health Services Authority created Pain Care BC and has improved the whole “triangle” of pain care, Hudspith said.

Hudspith segments the triangle into four parts — kind of like older iterations of the food pyramid. At the bottom, most people will be supported by free, low-barrier community and online supports, such as peer support, group and coaching programs. Those who need further care take a step up the triangle of support to meet with primary care providers. If people need further support, they are elevated to interdisciplinary or multidisciplinary pain clinics. At the very top of the triangle are specialty pain clinics run by a health authority, which help care for the patients with the most complex and challenging care needs.

Low-barrier supports can focus on pain neuroscience education, supported self-management and other strategies The Tyee recently spoke with pain researcher Cynthia Thomson about.

Specialty pain clinics would focus on specialized treatments such as spinal cord stimulators, which help override pain signals using a small electric current.

B.C. was the first province to introduce supported self-management, pain neuroscience education, peer support and low-barrier community programs, Hudspith said.

But now the province is lagging in investments for low-barrier community and online supports, and specialist care, she added.

Patients can live with pain for 20 years before they are diagnosed with chronic pain and wait months or years to access specialists, she said.

“We’re far behind provinces like Quebec and Ontario, where they have really invested in that top part of the triangle,” Hudspith said. “We’re very, very far behind in that regard.”

That’s a huge problem, because one in five Canadians will live with chronic pain in their lifetime that is so severe it disrupts their daily life, she said.

This includes kids suffering from juvenile arthritis, chronic migraines or injuries from sports, and adults and seniors suffering after car crashes, cancer and arthritis.

Chronic pain is defined as pain that persists after tissue has healed, or pain that lasts more than three months.

Pain is biopsychosocial, meaning the experience of pain is influenced by a variety of factors, including stress, sleep and “sandwiches” — in other words, how hungry a person is.

“It is really not just a physical thing,” Hudspith said. It’s real and is a chronic condition, she added.

And it’s often treated dismissively. People suffering from chronic pain are told they’re lazy, just trying to get off work on disability, or drug seeking, Hudspith said.

“People are disbelieved, invalidated, blamed and even criminalized,” she said. “If you’re living with arthritis or if you have cancer, you’re not also living with invalidation, disbelief, blame and essentially being told you’re crazy or have a character flaw. But people living with chronic pain are dealing with that burden on top of the experience of pain.”

A 20-year toxic relationship with pain

Keith Meldrum is all too familiar with that experience.

Forty years ago as a teenager, he drank alcohol and drove off the road, down an embankment. He was wearing only the waist strap seatbelt, which ended up around his stomach and tore him up internally as the car rolled.

He had emergency surgery and spent a week and a half in the intensive care unit. His body healed, but the pain persisted.

For 20 years after the accident, Meldrum had a “really unhealthy relationship” with his chronic pain.

“I was very, very adamant as a young adult that I was not going to let pain define me,” Meldrum told The Tyee. “I kept fighting it and pushing it back. All I did was create this sort of feedback loop of stress and anger that perpetuated the pain.”

When Meldrum sought medical help, he said doctors would tell him his pain wasn’t real or that there was nothing wrong with him. There was a real reluctance from doctors in the ’80s and ’90s to think of pain outside of tissue damage, he added.

Meldrum said he ended up in a pretty dark place and would wish he hadn’t lived through the accident.

And then, 15 years after his accident, he met Dr. David Hunt, who worked at the St. Paul’s Hospital Complex Pain Centre.

That interaction was “the first time somebody truly validated my pain as something real,” Meldrum said. “It didn’t change my relationship [with pain] overnight, but that was the spark that lit the fire for me to be able to find a different path.”

Meldrum ended up receiving a spinal cord stimulator. The stimulator reduced his pain by 25 to 30 per cent, which created “space” for him to realize he was exhausted with being angry, he said.

image atom
Pain Is in the Brain. And That’s a Good Thing
read more

He began thinking about what he could do, rather than thinking about what he couldn’t do.

“Since then, my quality of life has certainly improved. I’ve regained a lot more function because I stopped fighting against it,” he said.

How people think about chronic pain changes the way it feels, according to an Australian educational website. Another way to think of that: the brain can be retrained to make pain signals gentler.

The sooner people can start learning about the complex phenomenon of pain and access resources and education on what they can do to help themselves, the better, Meldrum said.

This is part of supported self-management, which can be enough for people to manage their pain. For others, it can work in concert with community supports and health-care supports such as physiotherapy or medication.

Canada’s complex relationship with pain

Canada’s relationship with pain has changed dramatically over the past few decades.

In the early 2000s, opioid prescription was widespread across North America. In a 2018 lawsuit, B.C., on behalf of Canada, accused pharmaceutical companies of downplaying risks and potential addictive qualities of opioids when marketing them to doctors. In 2023 Purdue Pharma, which sold OxyContin, settled for $150 million. The province is still pursuing the class action with “dozens” of other companies.

Canada was, and remains, one of the top opioid prescribers in the world, Hudspith said. There are a number of reasons for that, she added, including a “pill popping” culture where people believe medication will fix them; the influence of Big Pharma; and a health-care system where seeing a doctor for a couple of minutes is free but physiotherapy and psychology aren’t.

In 2015 and 2016 there was a “pendulum swing,” when doctors pulled back on prescribing opioids and highlighted how a multimodal approach was needed to treat chronic pain, Hudspith said.
image atom
This Medical Device Is a Chronic Pain Game-Changer
read more

But a multimodal approach hadn’t been built out yet, so pulling back on prescribing opioids was a bit like taking away the only tool in the tool box to treat pain, she said.

In 2019 the country launched the Canadian Pain Task Force, and in 2021 it released its action plan with its 150 recommendations.

And while the country has made huge strides, people living with chronic pain still face stigma and long wait times for supports and services, she said.

The provincial and federal governments are investing heavily in megaprojects, she added, while not doing enough to recognize the high rates of chronic pain suffered by people in the trades.

Anyone who thinks they may have chronic pain can visit Pain BC’s website for information and resources, or text and call Pain BC at 1-833-261-7246. The services are free and do not require coverage under the provincial Medical Services Plan.

People don’t have to prove their pain to access resources, Hudspith added. “It’s a big tent,” and everyone is welcome.  [Tyee]

Read the whole story
sarcozona
2 minutes ago
reply
Epiphyte City
Share this story
Delete

Doerkson Invited Young People to Stay. Now They Need Homes

1 Share
BC’s Conservative government should keep what works from the NDP’s policies.

Read the whole story
sarcozona
6 minutes ago
reply
Epiphyte City
Share this story
Delete

Immigration hand-wringing, unsigned editorial edition

1 Share

The Globe and Mail had an unsigned editorial yesterday morning, wringing their hands about the plan for those additional 200,000 permanent residents, and the usual lament about housing and so on. Nowhere did they mention that about a quarter of these temporary residents meant for permanent status are Hong Kongers and Ukrainians who are in the country. In their insistence on wailing and gnashing their death about the supposed shell game around the numbers, they falsely blame the Trudeau government for creating a “massive mess” in the system, and nowhere do they blame the premiers for a) demanding more immigration for labour shortages, and b) then doing fuck all about housing, healthcare, or education capacity to absorb anyone. And no, Trudeau didn’t make a mess. He responded to the signals (lest anyone forget conditions post-lockdowns), and other levels of government didn’t do their jobs.

The Globe and Mail editorial ignores that these 200,000 are largely Hong Kongers and Ukrainians and can't just go home, and that it's the provinces who have abdicated their responsibilities. Again.And of course, the usual suspects ignore the same things.www.theglobeandmail.com/opinion/edit…

— Dale Smith (@journodale.bsky.social) 2026-11-10T15:31:14.338Z

These people ignore reality and keep trying to turn this into an instance of "trust in the system" and "Trudeau bad" while absolutely ignoring the role of the premiers in all of this is—and let me repeat, they are responsible for housing, healthcare, education AND they *demanded* more newcomers.

— Dale Smith (@journodale.bsky.social) 2026-11-10T15:31:14.339Z

I'm just so fucking tired of the fact that the premiers remain blameless in the messes that they create. We're a federal system. Why can't our national legacy media outlets actually do their fucking jobs? This shouldn't be that hard.

— Dale Smith (@journodale.bsky.social) 2026-11-10T15:31:14.340Z

I absolutely loathe that this government uses Nigel Farage-esque "take back control" language in official immigration department releases. Meanwhile, these are the people that the Globe and Mail wring their hands about housing, and Mikal Skuterud thinks should just "outmigrate."

— Dale Smith (@journodale.bsky.social) 2026-11-10T19:44:45.435Z

To say that I have lost all patience with legacy media’s refusal to look at the facts and hold the premiers to account is an understatement. They may not be responsible for immigration levels (though they do have some input), but they are absolutely responsible for housing, healthcare, and education, and they have steadfastly refused to properly resource their systems, or do the hard work of reforms that are necessary to build more houses (especially when it comes to building new and maintaining existing social housing stock). And nobody holds them to account for these abject and ongoing failures. Nobody. And because legacy media will only both-sides everything, the provinces will cry poor, the federal government won’t push back and simply mouth some pieties about “cooperative federalism,” and the provinces get away with it again. Once again, I feel like I’m taking crazy pills.

This brings me to the plan to eliminate homelessness in ten years in the budget. I can promise you right now what’s going to happen, which is that the provinces are going to half-ass their obligations, there will be a mixed response from municipalities regarding their own obligations (such as a city like Ottawa doing as little as possible because the votes don’t come from downtown residents), and when it doesn’t work because the people responsible for the supports didn’t do their jobs, it will collapse in failure and everyone will throw up their hands and blame the federal government. We watched this play out with drug decriminalisation in BC. And when it does happen, absolutely nobody will hold the provinces to account for not doing their jobs, and I will once again be feeling like I’m taking crazy pills.

— Effin' Birds (@effinbirds.com) 2026-11-10T20:08:02.250Z

Ukraine Dispatch:

Russians pounded energy facilities in ten regions early Tuesday morning, and hit more power infrastructure in Kryvyi Riv early this morning. Renewed Ukrainian drone attacks on Russian oil refineries has reduced their capacity by thirty percent wince October.

Noteworthy:

  • The federal government has finally released details on who has been seconded to the Major Projects Office through the interchange programme.
  • In spite of new funding, the military has made cuts on soldiers attending Remembrance Day ceremonies, including who can attend unpaid.
  • Gary Ananadasangaree is signalling that he won’t entertain amendments to the (unconstitutional) lawful access bill currently in the Senate. 
  • Roland Paris calls on the Carney government to actually articulate what their principles are, as they keep touting “principled pragmatism.”
  • Colin Horgan lays out the federal government’s use of digital asbestos with inadequate rules, safeguards or supervision as Carney pushes even more adoption.

OP-ED – Canada must invest in AI now, before we miss our chance to lose all our money in the bubble crash, by Mark Carney

— The Beaverton (@thebeaverton.com) 2026-11-09T16:28:02.833Z

Want more Routine Proceedings? Become a patron and get exclusive new content. 

Read the whole story
sarcozona
11 minutes ago
reply
Epiphyte City
Share this story
Delete

The challenge of truly probabilistic programming

1 Share

Many years ago, Jouni and I wrote an unpublished paper called Fully Bayesian Computing:

A fully Bayesian computing environment calls for the possibility of defining vector and array objects that may contain both random and deterministic quantities, and syntax rules that allow treating these objects much like any variables or numeric arrays. Working within the statistical package R, we introduce a new object-oriented framework based on a new random variable data type that is implicitly represented by simulations.

A few years later we published an updated version of the paper under the title, Manipulating and summarizing posterior simulations using random variable objects. Here’s the background:

In the Bayesian paradigm, unknown quantities have probability distributions and are thus random variables. Observed values are just realizations of random variables, and constants may be thought of as random variables with point mass distributions. In mathematical notation, we deal with objects that are random variables, but in practice these objects are approximated by vectors of numbers, that is, simulations. Consequently, when programming for manipulating simulations of unknown quantities, we must write code to manipulate arrays of numeric constants.

And here’s the challenge:

Arrays of simulations are cumbersome objects to work with. Functions that work with vectors will not in general work with matrices, so special versions of the functions need to be written to accommodate matrices of simulations as arguments. For example, a scalar-valued random variable becomes a vector of simulations, and a random vector becomes a matrix of simulations. . . . The usual approach now is to use loops and vector-matrix computations to manipulate the matrix of posterior simulations. This approach is general but awkward and far from transparent . . .

As part of this effort, Jouni wrote a package in R called “rv” that allows direct manipulation of random variable objects, so for example if alpha and beta are random variables, each a vector of length J, and gamma is a scalar, then you can compute something like delta = (alpha + gamma)/beta, which would be a vector of length J. Internally, alpha, beta, and delta would be stored as S x K arrays, and gamma would be stored as an array of length S, where S is the number of simulation draws in your simulation frame, but the user would be able to work with these without having to keep track of that indexing; it would all be implicit.

The rv package was just a demonstration, but then more recently Paul Bürkner, Jonah Gabry, Matthew Kay, and Aki Vehtari implemented the idea in the “posterior” package in R. They call it rvar: The Random Variable Datatype. I still haven’t integrated rvar() into my Bayesian workflow, but I’d like to do it.

The point I want to make here is that this random variable datatype moves us closer to what I’d call “truly probabilistic programming.”

Here’s what I mean by that.

Stan (and Bugs, PyMC, etc.) are called “probabilistic programming languages,” characterized by Wikipedia as “based on the declarative specification of probabilistic models, for which inference is performed automatically.” Fair enough. In Stan, the variables defined in the parameters block, transformed parameters block, model block, and generated parameters block represent random variables with a joint density that is specified by the Stan program.

But, although this is called a probabilistic program as the term is used, it doesn’t fully feel like probabilistic programming in the sense of allowing me to grab random variables and work with them directly. I can do all that within the Stan program in the generated quantities block, but at a certain remove. Stan and other probabilistic programming languages are set up to run in batch mode: you specify a model and then the inference engine runs and spits out posterior simulations (or some other distributional summary).

To me, a truly probabilistic programming environment would allow me to interactively work with random variables, and to work with them as random variables, not as arrays of simulation draws. I want to be able to multiply two matrices without having to loop through the simulations. Part of this is about clean code, but more generally it’s about workflow. Any mathematical or graphical operations we can do on numbers, we should be able to do with random variables, with the simulations all hiding under the hood. Kind of by analogy to how we can do floating-point math on the computer without (usually) having to worry about how all these digits are being stored.

This will require tools such as rvar() and also some experience with the workflow. The payoff is . . . you could call it “better postprocessing of Bayesian simulations,” but I think that would understate the potential benefits of being able to work directl with uncertainty without that extra array dimension getting in your face at every step.

Read the whole story
sarcozona
13 minutes ago
reply
Epiphyte City
Share this story
Delete

Banking Needs To Be A Human Right

1 Share

This scourge continues to spread:

Poland just voted to EXPAND the government’s power to freeze your assets without a court ruling. Say the “wrong” thing online, and you could wake up to a FROZEN bank account. The bill lets the Interior Minister sanction anyone accused of supporting foreign interference or information manipulation aimed at Poland. Bank accounts, property, even crypto can be frozen instantly by administrative decision, and appealing to a court won’t automatically lift the freeze. It passed 240 to 202 last week.

In Britain and Germany multiple people have had their bank accounts frozen for supporting Palestine. When government isn’t directly involved banks often do the dirty work themselves, for example German banks debanking AfD politicians. The same happened to Farage in the UK. In Canada we had the government freezing accounts of the protestors against vaccines who parked their trucks in Ottawa. (I didn’t support the truckers, but at the time I said the accounts shouldn’t be frozen.)

As the economy moves more and more to electronic payments, being without a bank becomes more and more a sentence to homelessness. And even the small cash window is often closed In Germany, when the government de-banks you they also make it illegal to give the de-banked person any money so they can eat or pay rent.

This method of control makes organizing against the government almost impossible. It’s done to individuals and organizations. It needs to end. At the very least it cannot be something that is done by executive fiat but which requires a judge and jury and a trial. If the issue is avoiding someone transferring stolen money, then the amount that is frozen needs to be limited: enough must be left to pay bills, eat and so on and there has to be a mandatory maximum period the money can be frozen for.

Every individual should have a guaranteed bank account. The simplest way to do this is that when someone comes of age and gets whatever number the government uses to track citizens (like the social security number) then an account is opened by the central tax authority or a postal bank. A card is issued and the account is capable of all the normal things a bank account does. If you want retail outlets (not a bad idea) go back to postal banking. This account can never be taken away from someone, ever, even if they go to prison.

This needs to be a constitutional right, because increasingly you simply can’t survive without a bank account and governments cannot be trusted not to use petty powers to destroy their enemies of the day.

We’re about 2 weeks into our annual fundraiser. We’ve raised about $9,530 out of a $14,500 goal from 77 people. This blog is free for everyone to read, and we’ve got about ten thousand visitors a month. Of those about 6K are regulars.

The simplest truth of capitalism is that you get more of what you pay for. Money sends the message and resources required to do things. In most cases your power is tiny, one of millions, but this isn’t like that because the numbers and the need (to keep the blog and Ian running) are relatively small.

So if you value this blog, if it’s worth having around to you, please consider Subscribing or Donating.

Read the whole story
sarcozona
14 minutes ago
reply
Epiphyte City
Share this story
Delete

The babies missing from England’s heart surgery audit

1 Share

The surgical audit that helped make children’s heart surgery safer

Between 1984 and 1995, more babies died after heart surgery at the Bristol Royal Infirmary than should have, but it took far too long to realise because no systematic, comparable national data on outcomes was being collected. This isn’t just me saying it - the public inquiry which ran from 1998 to 2001 said so directly. One response was to start a new, mandatory, national database of every cardiac operation and interventional catheter performed on a child in the UK: the National Congenital Heart Disease Audit, which has underpinned quality assurance since the early 2000s.

It worked. Alongside surgical and intensive care advances, being able to see outcomes nationally and within hospitals as part of ongoing improvement programmes, has helped drive mortality down. Thirty day mortality after children’s heart surgery in the UK fell from 4.3% in 2000 to 2.6% in 2010, even though the complexity of operations rose. In the national audit’s 2025 report, the 30-day mortality for 2024/25 was just 1.3%. Painstaking national audit of this kind is something the NHS does very well.

But the audit misses a really important group of babies

But every audit has blind spots, and it’s important to understand them because otherwise we risk only focusing what we are measuring and forget about what we cannot see. A baby or child only enters the audit because a procedure happened. Babies diagnosed with a heart defect before or after birth who never had a procedure are not in there, and we have not been tracking what happens to them.

In April 2015, fifteen years after the national database of procedures began, Public Health England launched the National Congenital Anomaly and Rare Disease Registration Service (NCARDRS). NCARDRS registers congenital anomalies wherever in the pregnancy or the first years of life they are picked up: in babies born alive, in stillbirths, in miscarriages, and in terminations at any gestation. It covers more than a thousand different conditions, including congenital heart defects, and has the widest coverage of any congenital anomaly register in the world. It reached full national coverage in 2018.

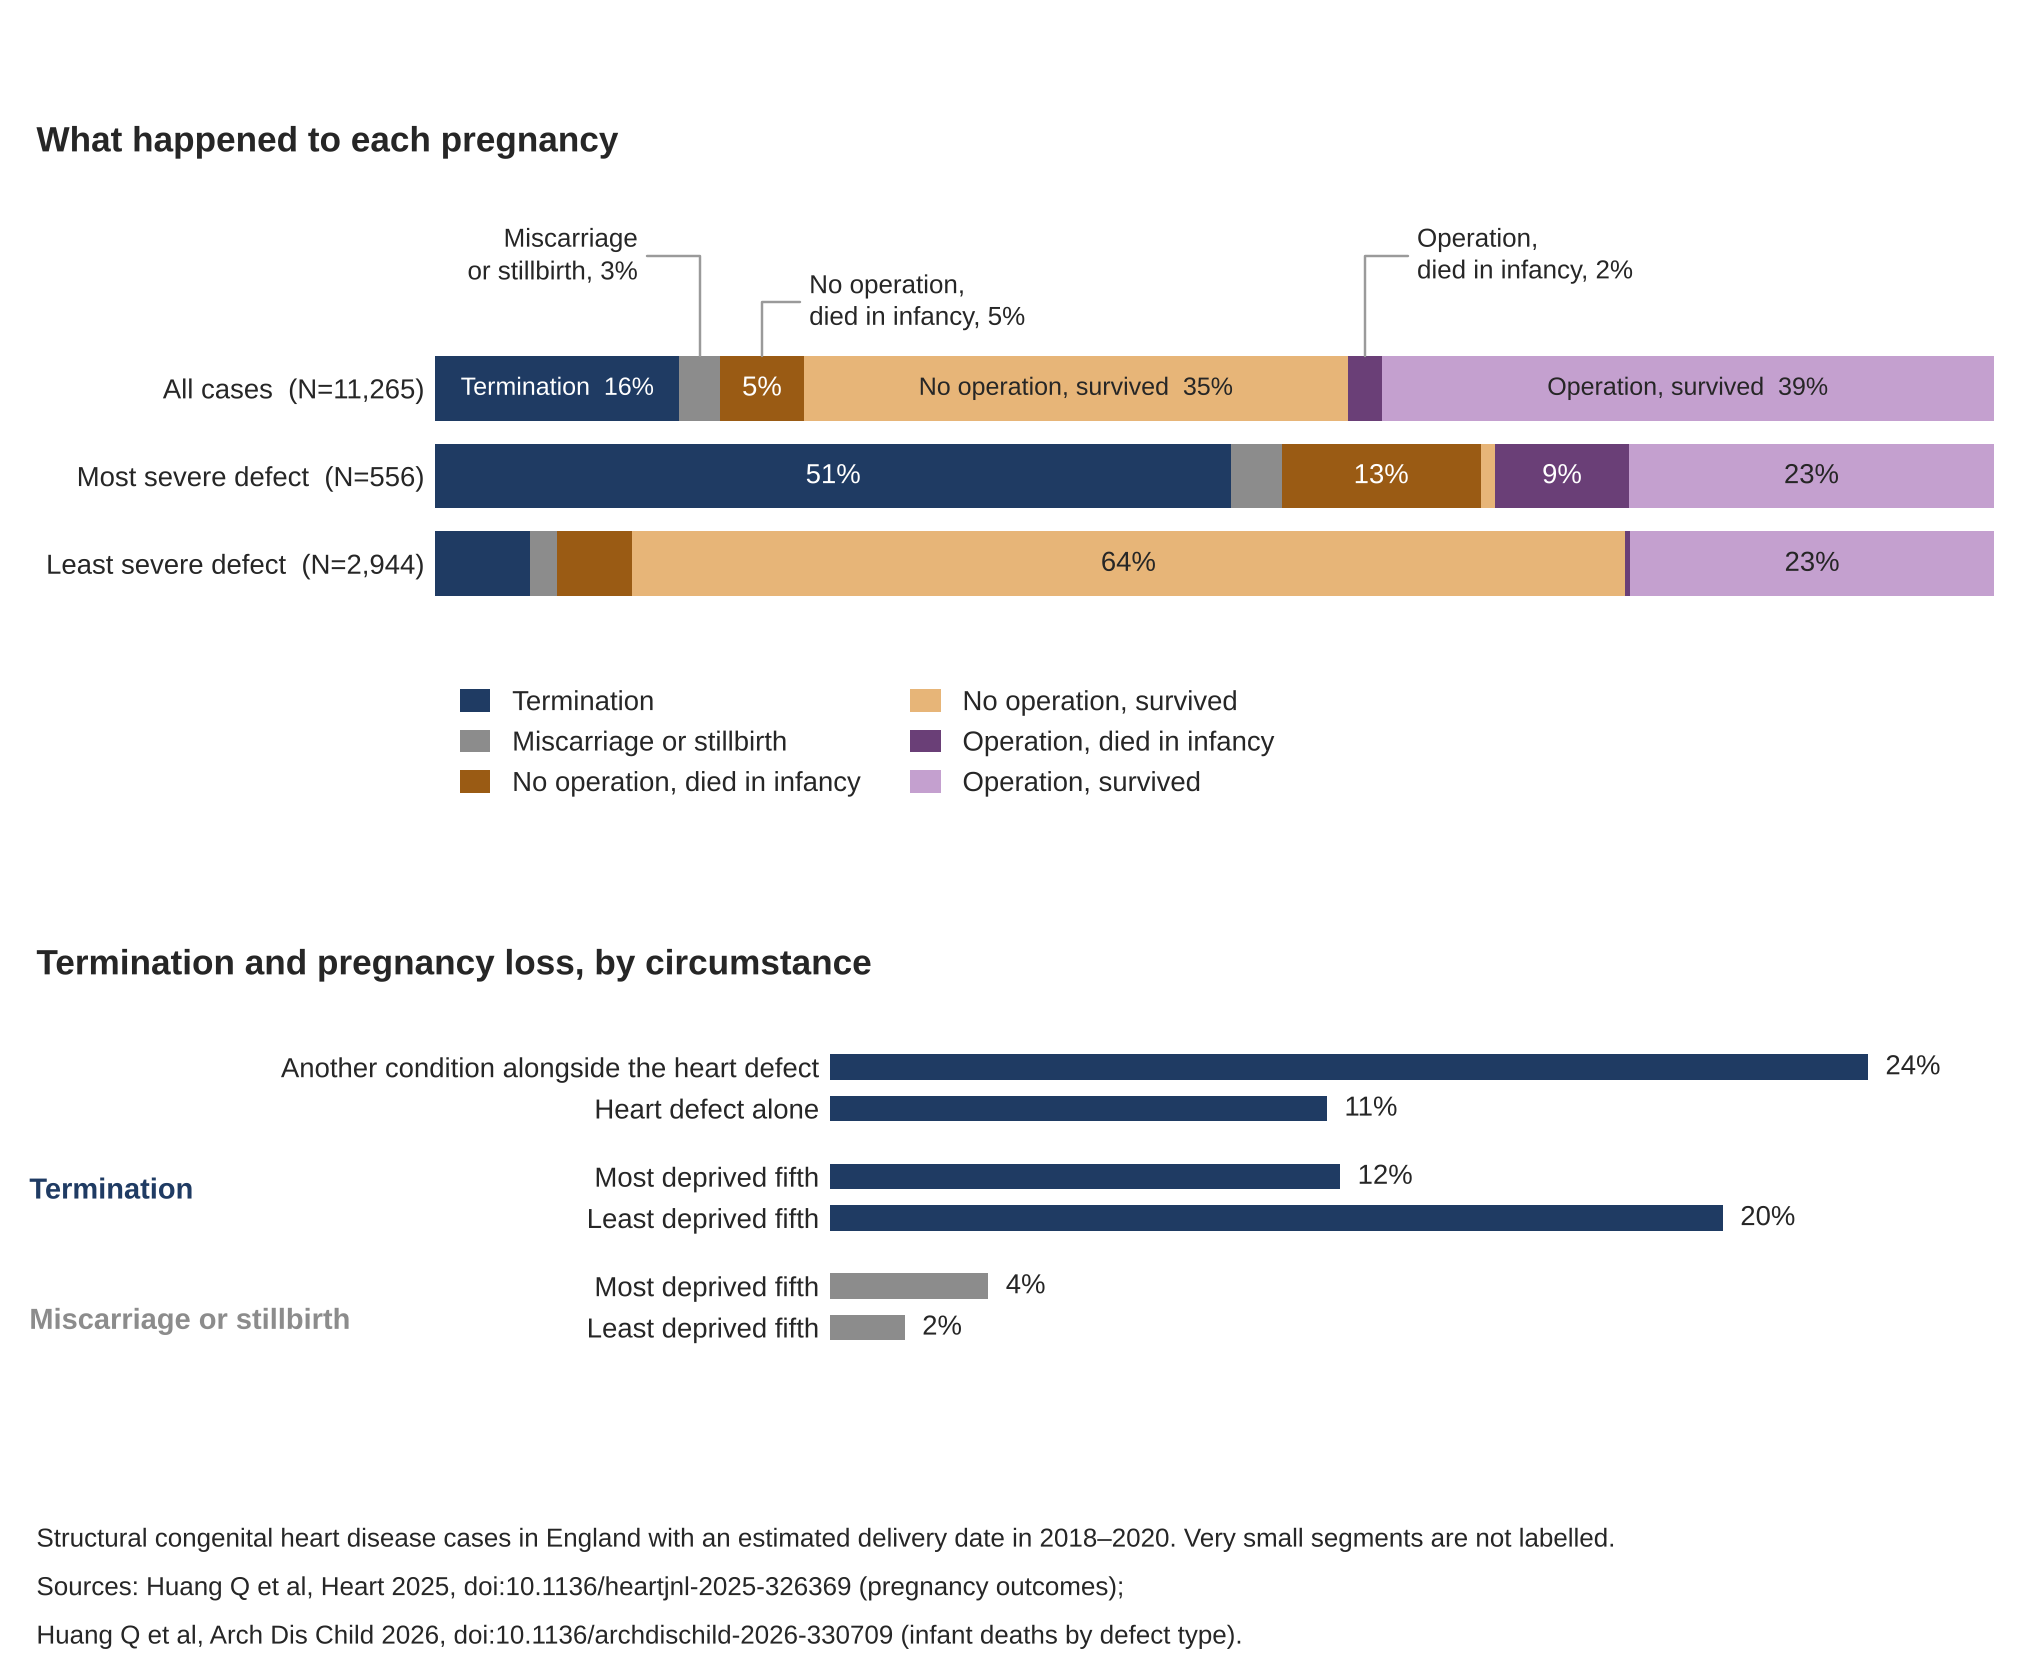
We saw an opportunity to combine the two datasets to understand for the first time what happens to foetuses and babies diagnosed with congenital heart disease. We linked the two datasets together as well as death registrations from the Office for National Statistics, and followed every detected case of structural congenital heart disease in England with an estimated delivery date in 2018 to 2020, from diagnosis to the first birthday, 11,265 foetuses and babies. Our second peer-reviewed paper has just been published, and I think the findings are both surprising and important. The first paper followed all feotuses and babies. The second looked in detail at the 9,033 babies born alive.

What happens after antenatal diagnosis

64% of cases were detected antenatally, with over 90% detected antenatally for the most complex defects. Detection was lowest (<30%) for defects that are hard to see on a four chamber scan or that develop later in pregnancy.

Of the 11,265 cases, 1,766 (16%) ended in termination and 295 (2.6%) in miscarriage or stillbirth. Termination was associated with severity, from 51% of foetuses with the most severe defect undergoing termination to 6% for the least severe. Termination was twice as likely where there was at least one other health problem alongside the heart condition.

Families in the least deprived fifth of neighbourhoods were nearly twice as likely to end the pregnancy as those in the most deprived fifth: 20% vs 12%. Foetal loss had the opposite association: 3.6% in the most deprived fifth vs 1.7% in the least.

This means that babies born alive are more likely to be born to mothers living in deprived communities.

Subscribe now

What happens to babies born alive with congenital heart disease

Of 9,033 babies born alive with a structural heart defect, 4,546 (50%) had at least one cardiac intervention before their first birthday. Among the 4,028 babies with a defect classed as severe, 77% had a cardiac intervention before their first birthday.

The other half had no procedure in that first year. Some babies are too well to need one yet. Isolated ventricular septal defect (a hole between the two main chambers of the heart) is the largest group in the non-intervened group: 2,016 babies with no intervention in the first year of life. Many of these holes close on their own or don’t need to be closed straight away, allowing babies to grow stronger before having surgery.

On the other hand, some babies are too sick or too complex to have surgery in their first year, or are on a palliative care pathway chosen with their families. Of 105 babies with the three most severe defects who had no intervention in their first year of life, 95 sadly died before their first birthday.

The deaths we are just not tracking

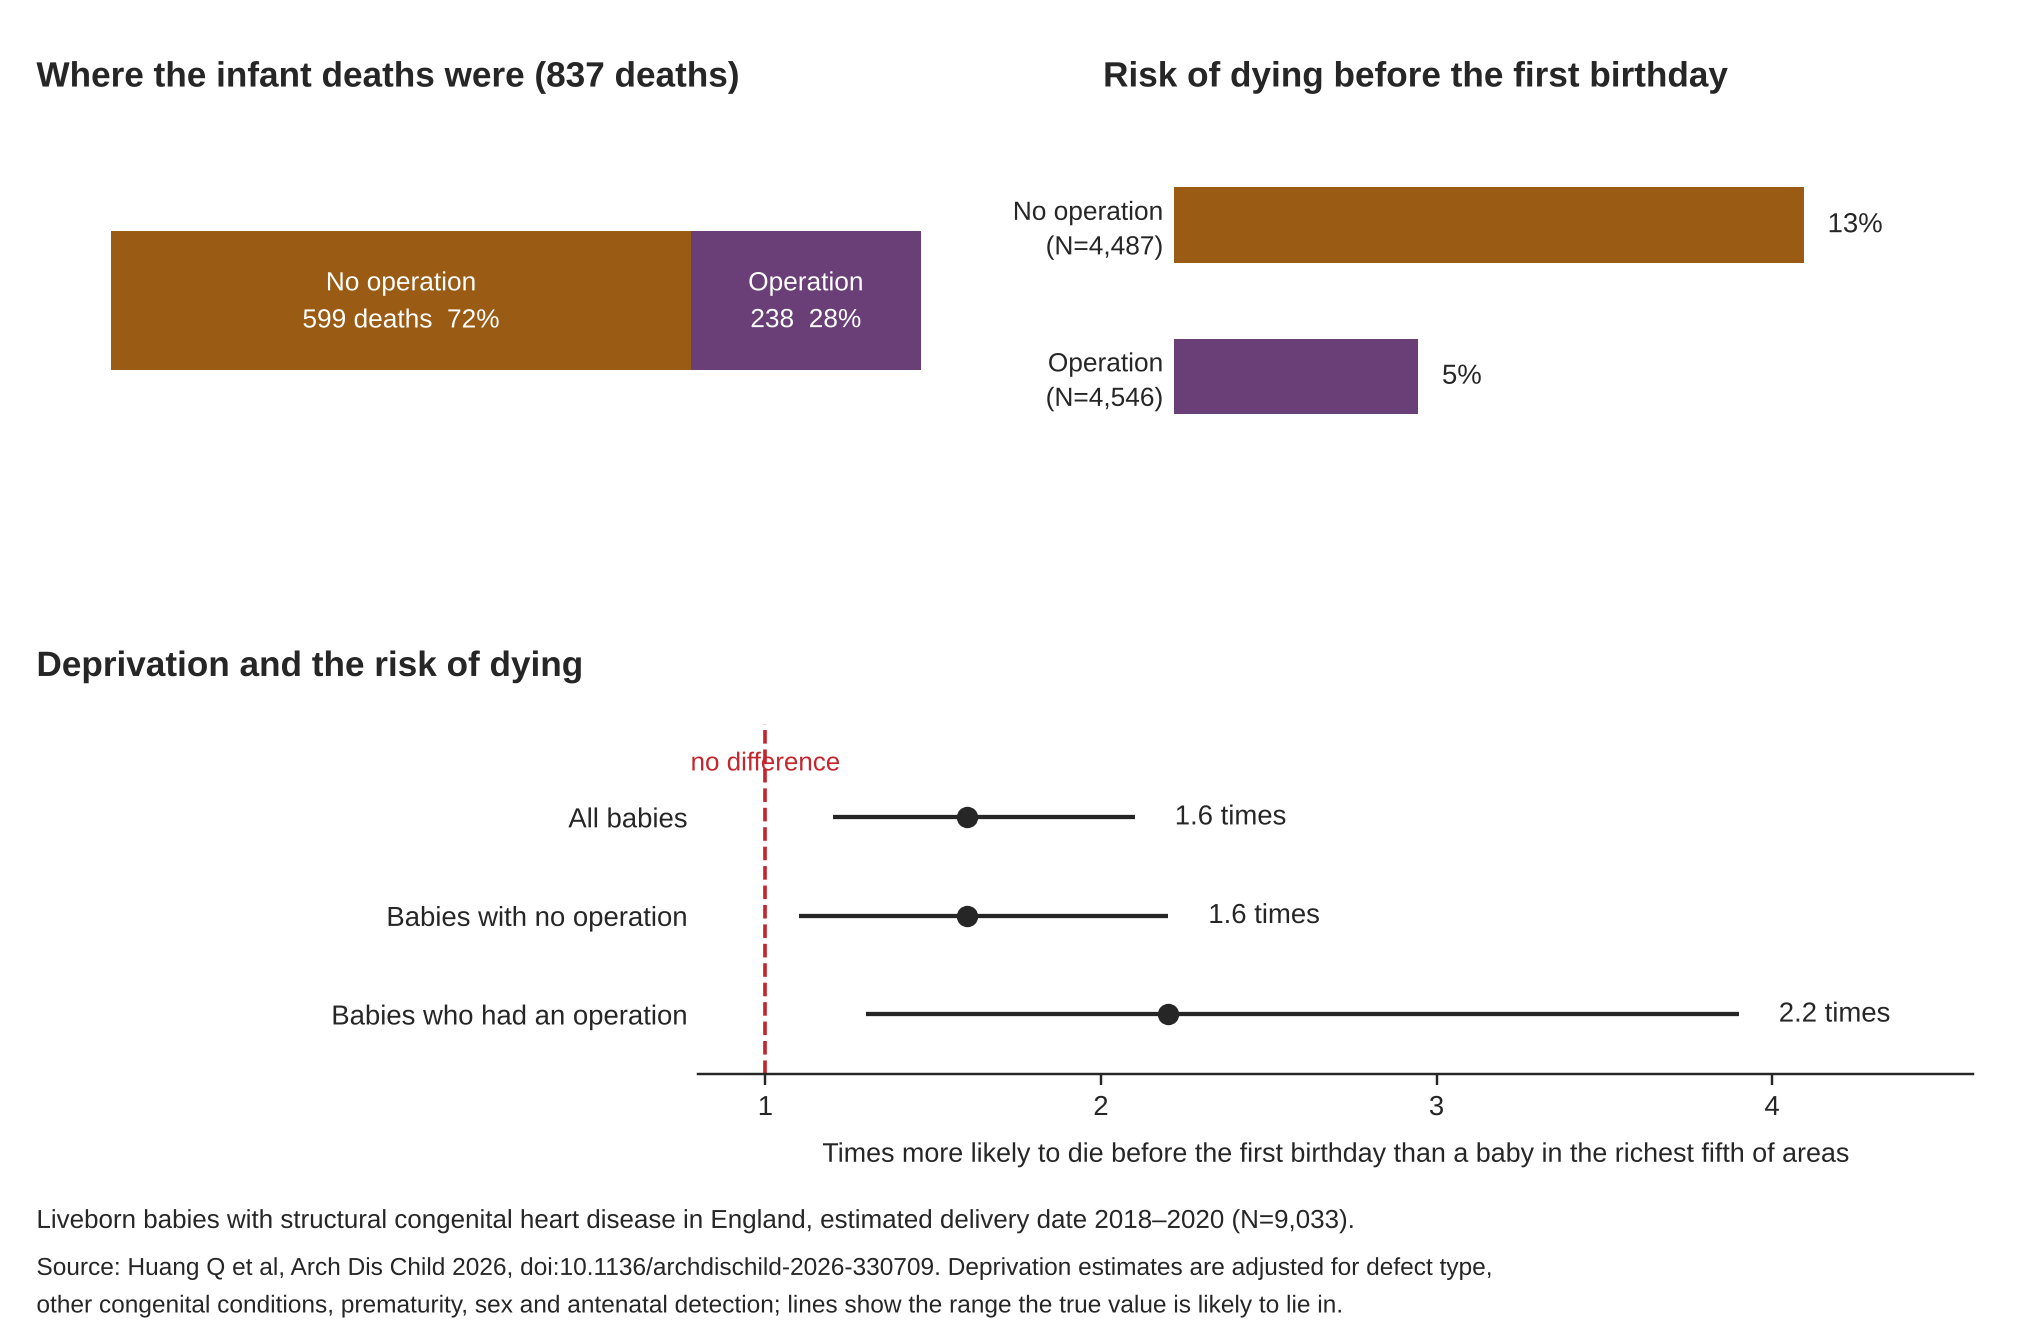
What our research really showed was the importance of looking at the whole picture – because looking just at babies who received an intervention (especially if looking only at deaths within a month of surgery), simply misses too much information. Overall, 837 of the 9,033 babies born alive died before their first birthday (9%). Of those deaths, 599 (72%) were in babies with no cardiac intervention, and so would not have been picked up in the national audit based on interventions. Infant mortality was 13% in the non-intervened group against 5% among babies who were operated on.

We tested whether impaired access to care was a possible explanation for the difference between deaths with and without an intervention in the first year of life. If it might be, we would expect to see that babies who died without an operation would have been less likely to have an antenatal diagnosis and more likely to be born in a more deprived area compared to those who died after an operation. We saw neither association.

Medical complexity does seem to be a likely explanation for the difference. Comparing deaths in babies without an operation to deaths after one, 60% vs 49% had an additional non cardiac congenital condition, and 50% vs 29% were premature (a big risk factor). This pattern holds across the spectrum of severity for defects.

Deprivation was also important. Babies born in the poorest fifth of neighbourhoods were about 60% more likely to die before their first birthday than babies in the richest fifth, once differences in the defect itself, other conditions, prematurity, sex and whether it was found before birth were accounted for. This was true whether the baby had a procedure or not. The data do not allow us to understand why, but they do suggest that this should be an area of future research focus.

The surgical audit was started to monitor surgical outcomes and to try to ensure that any concerns about quality of surgical care can be picked up quickly. But that means only looking at deaths within a short time of surgery and missing babies that died later after surgery (which could be for a number of reasons) or those not operated on at all. I believe that these latter deaths are important to track for two reasons: firstly providing families with better information about what might happen on first diagnosis, and secondly, so that the NHS can learn to improve outcomes for these babies. This could be by improving decisions around which babies receive an operation, by improving support for children and families who do not receive an intervention, or by improving support once babies go home after surgery, particularly for those living in more deprived communities.

So what next

Routinely report on the non intervention pathway. These babies and their families are receiving care, including palliative care, and to our knowledge their outcomes are not being systematically reviewed anywhere.

Understand more about why babies had no operation. Futility, parental choice, and a defect that simply did not need fixing yet are categorically different things that show up the same way in the data – to separate them and, importantly, understand them, we need new prospective research studies working with clinicians and families.

Understand what’s behind more deaths in deprived areas. We see significant differences between most and least deprived areas for termination rates, foetal loss, and in infant death with and without surgery. Understanding why is crucial if we want to improve outcomes for babies born in more deprived areas.

Keep (and expand) the surgical audit. Counting what happens to operated babies was, and is, a good thing and has helped drive improvements in survival for these babies. As mortality rates have come down, we should add other outcomes to the audit (such as complications after surgery, which has already started), to support services to keep improving.

I don’t often write about my academic research on Substack, but I thought this work was a really good example of how clinical audits can support improved care but also how important it is to try to understand the whole picture – and how different perspectives on the same data can really provide new insights.

Thanks for reading Making sense... of evidence, data, and the stories they tell! Subscribe for free to receive new posts and support my work.

Read the whole story
sarcozona
18 minutes ago
reply
Epiphyte City
Share this story
Delete
Next Page of Stories